DevelopingEM is a great conference, but it is just a conference, 5 days of education.
The real benefit from our events comes from people meeting people and cooking up schemes that provide lasting benefit.
Some examples include recurrent paediatric, ultrasound and trauma workshops across the Caribbean, increased connectivity between regional clinicians with mentors and educators in Australia and the USA, and ongoing mentoring of prehospital practitioners in Sri Lanka and Fiji.
The island nation of St Lucia in the Caribbean has become a bit of a poster child for this lasting benefit from a short conference.
Since the amazing Lisa Charles first presented on the development of emergency medicine in her home country St Lucia during our conference in 2013 there has been a stream of interactions partially fostered by meetings at DevelopingEM events.
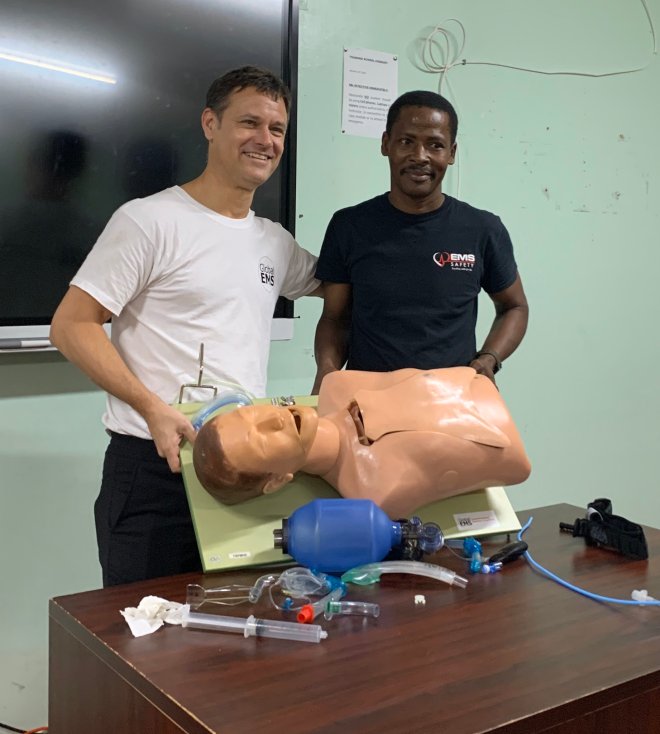
Jo Unger is a consultant anaesthetist and EMS Medical Director of the Berlin Fire Department.
He’s also our most devoted DevelopingEM international fan having been to all six of our international conferences. He even collects the wrist bands.
So how did an anaesthetist from Berlin end up collaborating with emergency physicians from Stonybrook in Long Island to provide a sustainable EMS training program in St Lucia.
Well it was a long process.
Jo had been involved in the Caribbean for a number of years.
Between 2009 and 2011 he worked in Guadeloupe at the Centre Hospitalier Universitaire, Pointe-A-Pitre both supervising and performing anaesthesia.
He attended DevelopingEM 2013 in Havana, Cuba where he met Lisa Charles from St Lucia.
In 2014 he came onto our faculty for DevelopingEM 2014 Brazil, in Salvador Da Bahia, being an integral part of the Trauma track as well as facilitating a De-escalation workshop during the conference.
In 2016 and 2017 he performed a Quality performance assessment in the Emergency Department of Victoria Hospital in St Lucia utilising an evidence based assessment tool of his own design.
In 2018 and 2020 he met and forged ties with an enthusiastic group of new emergency physicians from Stonybrook Health in Long Island at DevelopingEM Fiji and Colombia.
With this team he returned to St Lucia in 2021 to conduct a comprehensive EMS train the trainer course for first responders in St Lucia.
And so from brief conferences long standing connections and international collaboration have flourished.
We hope that this example inspires you to connect with like minded colleagues at DevelopingEM 2022 Darwin.
The conference will have a virtual capacity but in truth we hope that many of you will consider attending in person and expanding your international connections.
Perhaps there will even be long lasting friendships and collaboration that are again fostered providing benefit for remote and First Nations communities in this amazing part of the world.
You can register for the event here and we hope to see you in Darwin in September!
The workshops are based on the material produced by Matt, Mike, Jacob and Terren over the years for their Ultrasound Leadership Academy.
The approach is to provide excellent “pre-reading” (around 20 hours of topic based POCUS educational videos are part of the package sent to all workshop attendees) and maximal time on probe under direct expert instruction during the workshop.
This year Terren leads an international team of experts providing another amazing POCUS workshop experience during DevelopingEM 2022 in Darwin.
Jacob and Terren have consolidated the excellence of Ultrasound Podcast into their own venture- CORE ULTRASOUND– and they continue to model their workshops on the incredible Castlefest concept.
In 2022 they will be assisted by local experts including Nadi Pandithage a POCUS enthusiast based in the host city Darwin, and Angelo Abeywickreme from NSW. This will be Angelo’s 4th time assisting us with Ultrasound.
This workshop always sells out fast and registration will be open soon so get in quick!!
Core Ultrasound Workshop SEP 26 and 27, 2022 during DevelopingEM 2022 Darwin.
Jacob Avila showing just how far the Ultrasound Faculty will go to provide the best POCUS training experience.
On March 11, 2020 the World Health Organisation (WHO) officially announced a global pandemic that has changed our lives forever. It was also the last day of our Colombian event, DevelopingEM 2020, and in fact the WHO announcement was during a very pertinent presentation on COVID19 by Dr Ben Wyler. As we all headed home to periods of quarantine and busy workplaces the future of conferences and DevelopingEM was uncertain. The subsequent 18 months has seen enormous changes for all of us.
Lockdowns have given us plenty of time to think about the future of DevelopingEM and we believe there remains a place for a mostly live and interactive conference focussing on the development of emergency medicine. People meeting people has been the core benefit of our events and so many long standing and productive relationships have occurred as a result of DevelopingEMers meeting one another.
Next week we are formally announcing our plans for next year, DevelopingEM 2022 Darwin, and ahead of the announcement we wanted to reintroduce DevelopingEM as an organisation.
DevelopingEM is a little venture Sanj Fernando, Lee Fineberg and myself started about 10 years ago and DevelopingEM 2022 will be our eighth event.
DevelopingEM Ltd is a not for profit venture with a unique financial model.
On average greater than 90 percent of our funding comes from the registration fees of attendees from privileged situations, often where there is individual access to substantial study leave funding.
This funding not only pays for the organisational aspects of each event but, with careful budgeting, it allows funding to be directed towards subsidising the attendance of clinicians from host nations and regions.
The absence of a requirement for medical industry funding gives us organisational independence and there is no influence from industry bodies on our ethos and direction.
We aim to hold a regular regional conference in a situation where emergency medicine is rapidly evolving.
The educational approach is centred on the provision of excellent clinical information aimed at the senior clinician allowing all attendees to take home clinical pearls to their next clinical shift.
The core conference has tracks focussing on Adult Emergency Medicine and Critical Care, Paediatric Emergency Medicine and Trauma Care.
These core tracks are teamed with sessions focussing on the development of emergency medicine globally as well as sessions determined by the host partners.
Over the years we have had a number of enthusiastic partner organisations.
We have a range of workshop providers depending on the needs and requests of our regional partners.
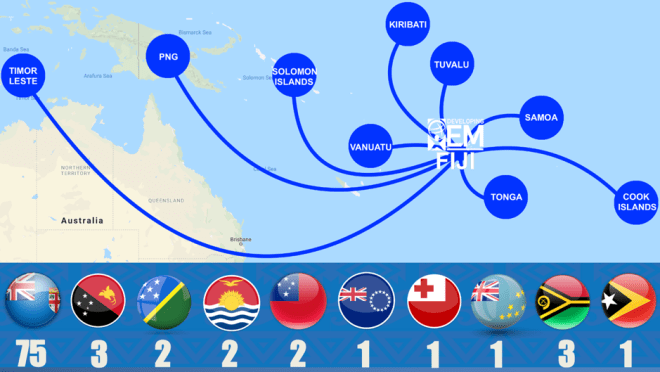
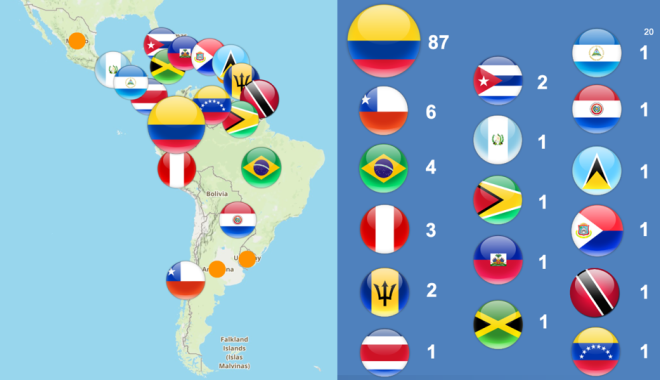
DevelopingEM 2022 will be our eighth event with previous events in Sydney, Cuba (twice), Brazil, Sri Lanka, Fiji and Colombia.
Over that time we have sponsored the attendance of over 600 regional clinicians who, depending on the setting, have paid anything from zero to ten percent of the registration fees of an international delegate.
The last 3 conferences have seen this delegate support become a much more organised venture with local and regional delegates not only mostly funded from a registration point of view but also receiving accommodation and travel assistance.
We remain very proud of this aspect of DevelopingEM.
One of the other achievements, which was less anticipated, were the longer-term effects of a broad range of clinicians coming together.
The opportunity that the events have provided for like-minded people to meet has resulted in lasting relationships that have resulted in long standing benefits across the regions where the conferences have been held.
Some examples include recurrent paediatric, ultrasound and trauma workshops across the Caribbean, increased connectivity between regional clinicians with mentors and educators in Australia and the USA, and ongoing mentoring of prehospital practitioners in Sri Lanka.
The benefits have certainly not been unidirectional, and we have been taught much by our regional colleagues.
Perhaps the most acute lesson is just how lucky we are here in Australia.
We in Australia are monumentally privileged in global terms to have the health care systems and working conditions that we enjoy.
Despite having a luxurious health care system, the explanation of the benefits of different systems from around the globe demonstrates that we also have much to learn about how to maximise the benefit of an emergency medicine system.
We have learnt how the Cuban system achieves the same health outcomes as Australia at one eighth of the cost.
We have seen how developing an emergency system from the ground up in Sri Lanka allows that system to focus on patients with actual emergencies.
Just because we have it good doesn’t mean we cant learn to be better, to be efficient and to be more focussed.
We have also been taught what it is actually like being an emergency clinician in a different system.
Emergency clinicians from around the globe have explained how they battle illness in working conditions we can barely fathom, with enthusiasm and without complaint.
These experiential presentations have been a core of our conferences and it has been an absolute privilege to learn from wonderful clinicians from around the world.
One of our Brazilian colleagues, Daniel Schubert, related recently what a 12 hour shift in an ED in Rio looks like.
Dan described the following patient selection from a recent shift and I think most clinicians in Australasia would struggle to rack up similar patients in years of practice.
In one average shift Dan treated patients with
Miliary Tuberculosis
a Type A Aortic Dissection
a Traumatic and Expanding Neck Haematoma
High Cervical Fractures and Neurogenic Shock
Cardiac Arrest
Severe Closed Head Injury- GCS 5
Hepatic Encephalopathy (also COVID positive)
Gunshot wounds (3 patients)
All this with the hospital supply of Ketamine exhausted and N95 masks in such short supply that staff were personally decontaminating their masks to reuse on subsequent shifts.
Similarly Carla Rey Navarro from Chile related how she was part of teams created during the pandemic to move intubated patients in Ebola style iso chambers, six at a time, in the back of a Hercules aircraft. This effort was to reduce the strain on the intensive care units in Santiago as the initial waves of the pandemic battered the capital.
She has also had to manage paramedics being injured whilst trying to care for patients in the middle of street protests, as well as organising the fire related evacuation of a 400 bed Santiago hospital . All this is the middle of a pandemic which has resulted in an enormous impact upon Chile.
Connecting with and learning from intelligent, dedicated colleagues like Daniel and Carla has been one of the amazing personal highlights of DevelopingEM.
So what’s next for DevelopingEM, a conference where the face to face dynamic is core?
Well COVID 19 has meant some changes for us.
In 2022 we were looking to combine with the African Federation for Emergency Medicine (AFEM) and conduct back to back conferences in Ghana, where there are rapidly evolving emergency medicine systems.
Both organisations remained excited about a joint venture but mid-way through 2020 it became clear that that even by late 2022 a live conference in Africa had no chance of happening.
It was a difficult realisation as we had been trying to get our event to the continent for a number of years.
We haven’t abandoned the idea and at this stage both AFEM and DEM are going to look at the possibilities for an African event in 2024.
So what to do instead?
Well for many years we had discussed the idea of a conference in Australia perhaps with a focus on First Nations Healthcare, and with COVID changing the face to face conference experience an event in Australasia now seemed a feasible and valuable option.
National and Local partners agreed and we look forward to them contributing hugely to the event.
There are differences and similarities between international developing emergency medicine situations and the Rural, Remote and First Nations critical care that are present within the Northern Territorian context.
So even though this will be a local conference we think that DevelopingEM 2022 Darwin easily fits within the aims and objectives of our organisation.
We hope during the conference to have a major focus on the challenges and opportunities of First Nations Critical Care and negotiations to work out how to appropriately integrate this topic into the platform are ongoing.
Lee, Sanj, I and the entire team are really excited about the possibilities DevelopingEM 2022 Darwin will hopefully bring.
We are also very enthused at the prospect of seeing you, our DevelopingEM family, again.
Stay tuned for our formal announcement next week and if you would like to be included on our mailing list to get regular updates as we move forward, please let us know.
We also discussed approaches to post vaccination symptoms particularly related to headache and CVST. There has been an excellent discussion of this phenomenon by the St Emlyn’s Blog and they include some guidelines from RCEM as part of the discussion.
April Kam, our Paediatric EM and Critical Care track lead, spent some time with us this week to discuss COVID 19 in the Paediatric population.
April is an Associate Professor in the Department of Pediatrics and the Director of Research and Quality for the division of PEM at McMaster University in Hamilton, Canada.
She has an interest in global health education and has worked around the world.
We are very lucky to have her expertise and energy devoted to DevelopingEM and in March she led a fantastic group of Paeds EM specialists for the 2020 conference in Cartagena, Colombia.
You can check out all the 2020 conference presentations from April and her team (Nate Kupperman from UC Davis, Viviana Pavlicich from Paraguay, Camilo Gutierrez from Kids National in DC, Tanya Solana from Sick Kids Toronto, Laura Galvis from Colombia and Suzanne Beno also from Sick Kids Toronto).
Today April gives us a Canadian and global perspective on how the COVID 19 Pandemic is playing out in Paediatric Emergency Medicine.
In this interview we discuss the prevalence of illness, some of the options for treating the respiratory form of the illness and also describe the evolving knowledge on the inflammatory and vascular forms of the illness in children.
We think you will agree that Paediatric COVID is a fascinating and evolving situation.
Check our all the references April mentioned here.
Hector is an Emergency Physician working in critical care at the Hospital Vivian Pellas in Managua.
He is a spokesman for the Nicaraguan Association of Emergency Medicine (ANME) and the ACEP Liaison for Nicaragua.
Hector attended our DevelopingEM 2020 conference in Cartagena and presented on the development of emergency medicine in Nicaragua.
Over the years we have had many fascinating presentations on the struggles colleagues have faced in the development of our specialty, emergency medicine.
The challenges faced by practitioners in Nicaragua is multifactorial and intertwined with a complicated political situation in the country.
This context is something that few of us have to calculate when advancing the expertise of our workplace.
Hector’s presentation analysed the development of EM within this overall context.
You can see Hector’s DEM2020 presentation in Spanish here.
Our follow up interview discusses the challenges that COVID 19 has brought to this setting.
Many of us have only a cursory understanding of Nicaragua and so here is some basic information on the country and its political situation.
Geography
Nicaragua is in Central America bordering Honduras to the north and Costa Rica to the South with both a Pacific and Caribbean coast.
Population
Nicaragua has a population of a little over 6 million with 87% of this population being under 55 years of age.
60% of the population are urbanised with 1 million people living in the capital Managua
Health statistics
Life expectancy at birth
74.2 years
(Australia 82.7 / USA 80.30 / Costa Rica 79.20 / Honduras 74.60)
Maternal mortality rate
198 deaths / 100,000 live births
(Australia 6 / USA 19 / Costa Rica 27 / Honduras 65)
Infant mortality rate
16.5 deaths / 1,000 live births
(Australia 3.1 / USA 5.3 / Costa Rica 7.5 / Honduras 14.6)
Current health spending
8.6% of GDP
(Australia 9.2% / USA 17.1% / Costa Rica 7.3% / Honduras 7.9%)
Physician density
1.01 physicians / 1,000 population
(Australia 3.59 / USA 2.59 / Costa Rica 1.15 / Honduras 0.31)
Hospital bed density
0.9 beds / 1,000 population
(Australia 3.8 / USA 2.9 / Costa Rica 1.1 / Honduras 0.7)
Major infectious diseases
degree of risk- high for food or water borne disease (including bacterial diarrhoea,
Hepatitis A and Typhoid fever)
and vector borne disease (including dengue and malaria)
(Costa Rica- degree of risk- intermediate / Honduras- degree of risk- high)
History
The Pacific coast of Nicaragua was settled as a Spanish colony from Panama in the early 16th century.
Independence from Spain was declared in 1821 and the country became a fully independent republic in 1838.
The dictatorship of General Zelaya began in 1893 but he was deposed with the help of United States (US) troops in 1909 marking the start of a prolonged period of US involvement in the affairs of the country.
Over the next decade the US established military bases in the country.
Guerrillas led by nationalist Augusto Sandino, after whom the Sandinista movement is named, campaign militarily against the US military presence and were part of the reason for a US withdrawal from the country in 1933.
Sandino was assassinated during peace talks in 1934 on the orders of National Guard commander General Anastasio Somoza Garcia.
General Somoza was elected president not long after in 1937, heralding a 44 yearlong rule by his family.
The Sandinista National Liberation Front (FSLN) is founded in 1961 and identified as a nationalist, socialist and anti-imperialist organisation, whose objective was the seizure of political power through the destruction of the bureaucratic and military apparatus of Somoza’s dictatorship.
In 1978 the assassination of the leader of the opposition parties triggered a general strike and brought together moderates and the FSLN in a united front to oust Somoza.
Violent opposition to governmental manipulation and corruption spread to all classes during 1978 and resulted in a civil war that brought a civil-military coalition, spearheaded by the Sandinista guerrillas, led by Daniel Ortega Saavedra, to power in 1979.
The FSLN government redistributed the vast Somoza family land holdings and promoted radical changes to education and healthcare.
However, it was their anti-imperialist, anti-capitalist and pro Cuban and Bolivarian identity that attracted the ire of the US which systematically commenced a program to remove the FSLN from government.
The Australian journalist John Pilger visited the country at this time and his insightful documentary can be seen here.
This US effort to unseat the FSLN was centred on military support for the anti-Sandinista contra guerrillas, but also involved the mining of Nicaraguan harbours and the enforcement of an economic embargo against the country.
These measures were responsible for enormous hardship and violence within the country and were a contributor to the FSLN losing free and fair elections in 1990 where they relinquished power to the democratically elected opposition coalition.
What followed was a difficult period that saw a gradual reduction in paramilitary violence but also increasing debt and corruption.
After losing further elections in 1996, and 2001, former Sandinista President Daniel Ortega was elected president in 2006, 2011, and most recently in 2016.
This new Sandinista period is a vastly different period to the 1980s with election wins coming at the cost of compromise for many of the FSLN core beliefs.
There have been coalitions with ex contras, rapprochement with the Catholic Church (including support for a ban on abortion by the FSLN), and new accords with the IMF.
Whilst there have also been reintroduction of free education and literacy programs, as well as Zero Hunger programs, and corruption crackdowns, there has also been a reduction in public financial accountability, a freeze on the wages of teachers and health care workers (already the lowest in Central America) and suspect constitutional change allowing Ortega to continue as President beyond the usual two terms previously allowed.
Concerns about an increasing authoritarianism had been growing internally and were recognised by Amnesty International in 2018 when responses to protests against the government outlined Amnesty concerns.
These concerns are more expansively explained here but centre on the reduction of interaction with international agencies scrutinising human rights, an appreciable reduction in the freedoms of expression and assembly, the use of the legal system to prosecute political opponents, increased state sponsored violence and government targeting of journalists, human rights defenders and local NGOs.
In the last 2 years there have been mass protests over wages and social security changes that have morphed into general denunciations of the ruling party and system especially after the very violent responses to the original protests.
The political situation in that period has been a factor behind the nearly 90,000 Nicaraguans who have recently fled the country.
It is into this complicated and multifaceted situation that COVID 19 arrived in March.
Hector’s perspectives on the current situation are fascinating and we remain very grateful for his time and expertise.
If you would like to help in efforts to supply PPE and other equipment then please consider joining with DevelopingEM in donating to the efforts of FNE International.